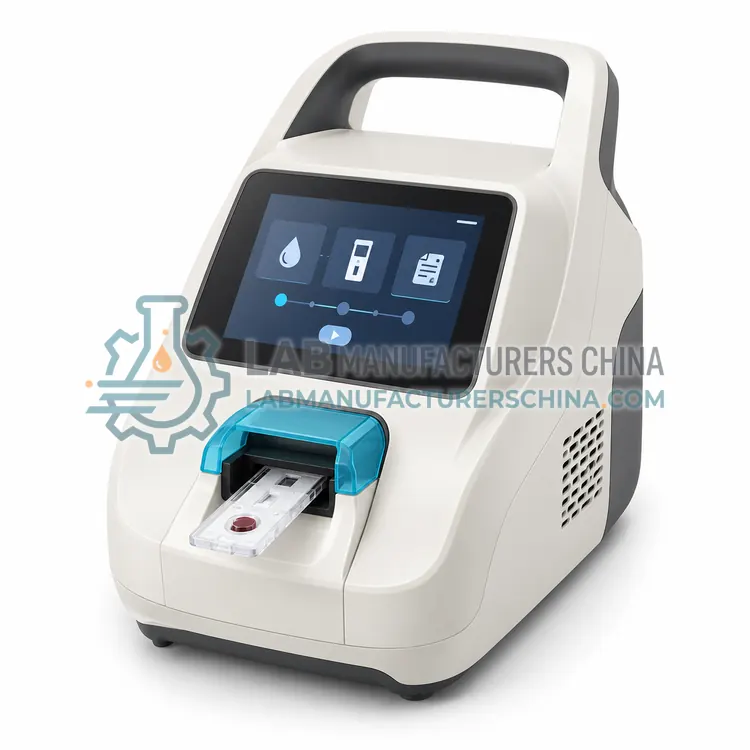
Automated Aliquotting Station for Diagnostic Specimens
诊断样本自动分装工作站
- SKU SAM-0001
- Sample Preparation
- CE (to be confirmed)
- ISO 13485 manufacturing (to be confirmed)
- NMPA class II registration (to be confirmed)
Price on request — FOB / CIF quoted per order
Prices depend on configuration, quantity and destination port.
Key specifications
| Aliquot volume range | 0.2–10 mL programmable |
|---|---|
| Volume accuracy | ±2 % at 1 mL |
| Tubes per primary specimen | 1–6 secondary tubes |
| Throughput | 60–150 aliquots/h |
| Primary tube types | 13–16 mm diameter serum and EDTA tubes |
| Tip handling | Disposable tips or washed fixed probe |
Request a quote Download brochure · to be provided
By Lab Manufacturers China Technical TeamLast reviewed Standards: ISO 15189, ISO 15190, CLSI GP16
What is the Automated Aliquotting Station for Diagnostic Specimens?
An automated aliquotting station splits serum, plasma or other diagnostic specimens from primary tubes into labelled secondary tubes with defined volumes. It suits laboratories that archive specimens for repeat testing and want to avoid manual pipetting errors and cross-contamination.
Overview
The station reads the primary tube barcode, aspirates a measured volume with a disposable tip or a fixed probe, dispenses it into one or more secondary tubes, and prints or applies labels that carry the specimen identifier, aliquot number, date and storage location. Liquid-level detection prevents aspiration of cells or clots, and conductivity or pressure sensing verifies the delivered volume for each aliquot. Programs can be defined per specimen type, with different volumes for serology, molecular testing and archiving. Carryover is controlled by tip changes or by wash cycles and should be verified with high-low sequences. Because each aliquot becomes an independent record, the software must be able to report which primary specimen each derived tube came from.
How does it work?
Diagnostic sample preparation changes a specimen so that a downstream assay can measure it reliably. Serum and plasma are separated from cells by centrifugation and then aliquoted into labelled tubes, which reduces thaw cycles and cross-contamination during archiving. Some serology and molecular workflows require heat inactivation, typically at 56 degrees Celsius for thirty minutes, to reduce infectivity before handling. Solid or viscous specimens such as stool, sputum, swabs and tissue must be homogenised, liquefied or extracted into a buffer so that target organisms or analytes are released uniformly. Fecal immunochemical tests need a defined sample mass mixed with buffer, and blood film preparation requires a controlled spread and stain so that cells can be examined morphologically. Each step influences the analytical result, so volume accuracy, temperature control and traceability matter as much as in the analytical instrument itself.
What are the key features?
- Barcode reading of primary tubes with label printing for aliquots
- Liquid-level and clot detection during aspiration
- Programmable volumes per specimen type and destination
- Disposable tips or washed fixed probe for carryover control
- Volume verification by pressure or conductivity sensing
- Full traceability between primary and derived specimen identifiers
What are the technical specifications?
A typical automated aliquotting station for diagnostic specimens configuration offers aliquot volume range of 0.2–10 mL programmable, volume accuracy of ±2 % at 1 mL, tubes per primary specimen of 1–6 secondary tubes, throughput of 60–150 aliquots/h, primary tube types of 13–16 mm diameter serum and EDTA tubes and tip handling of Disposable tips or washed fixed probe. Values are indicative of the product class; the exact figures for each configuration are confirmed on the quotation and the calibration documents supplied with the instrument.
Which applications is it used for?
The Automated Aliquotting Station for Diagnostic Specimens is used in serum banking for repeat serology, molecular testing specimen archiving, clinical trial sample division and reference laboratory specimen distribution. Across the wider Sample Preparation class, laboratories also deploy it for serum and plasma aliquotting for serology and molecular testing, heat inactivation of serum before batch serology and stool and sputum processing for infectious disease testing.
Which standards and certifications apply?
Relevant standards and methods include ISO 15189, ISO 15190, CLSI GP16, CLSI M29, CLSI EP05, IEC 61010-1 and IEC 61010-2-101. Certification candidates for this model are CE, ISO 13485 manufacturing and NMPA class II registration; each is to be confirmed for the specific configuration before shipment, and certificates are supplied only where they have been issued.
Verify each device at installation with gravimetric volume checks, temperature mapping and, where relevant, recovery or uniformity studies using spiked specimens. Write procedures that define specimen acceptance, batch size, temperature and time limits, and the identification of each aliquot, because traceability between the primary tube and derived aliquots is frequently examined during accreditation. Clean and decontaminate surfaces, rotors and homogenisation chambers after each batch, and use sealed or disposable components where aerosols are a risk. Record maintenance, calibration and validation data, and review temperature records for heat inactivation and incubation steps. Treat all specimens, consumables and waste as potentially infectious.
How do I select the right Automated Aliquotting Station for Diagnostic Specimens?
Specify this station when specimens are frequently archived or distributed, or when manual aliquotting is a recognised source of labelling errors. In the RFQ state the specimen types, the required aliquot volumes and tolerances, the number of tubes per specimen, the labelling format used locally, and whether the LIS can accept the derived identifiers.
How does it compare with other Sample Preparation variants?
Start from the specimen types you receive and the assays that follow, since a device is only useful if its process matches the downstream kit requirements. For aliquotting, check the number of tubes per primary sample, the dead volume, the liquid class accuracy for viscous specimens and the labelling method. For heat inactivation, confirm the temperature uniformity across the bath or block, the capacity per batch and whether a lid is needed to limit evaporation. For homogenisation, choose between bead milling, rotor-stator and paddle systems according to specimen hardness and the need to keep analytes intact. For fecal and blood smear preparation, confirm the sample mass or film quality specification. In all cases, ask for process validation data and confirm that consumables are available locally.
Full specifications
| Aliquot volume range | 0.2–10 mL programmable |
|---|---|
| Volume accuracy | ±2 % at 1 mL |
| Tubes per primary specimen | 1–6 secondary tubes |
| Throughput | 60–150 aliquots/h |
| Primary tube types | 13–16 mm diameter serum and EDTA tubes |
| Tip handling | Disposable tips or washed fixed probe |
| Labelling | Printed barcode labels with date and aliquot number |
| Data storage | 50,000 aliquot records |
| Interfaces | LAN with LIS connection and barcode output |
Indicative values for this product class. Final specifications are confirmed on the quotation and in the calibration documents supplied with the instrument.
Applications
- Serum banking for repeat serology
- Molecular testing specimen archiving
- Clinical trial sample division
- Reference laboratory specimen distribution
Key features
- Barcode reading of primary tubes with label printing for aliquots
- Liquid-level and clot detection during aspiration
- Programmable volumes per specimen type and destination
- Disposable tips or washed fixed probe for carryover control
- Volume verification by pressure or conductivity sensing
- Full traceability between primary and derived specimen identifiers
Frequently asked questions about Automated Aliquotting Station for Diagnostic Specimens
Disposable tips eliminate carryover at the cost of consumables, while fixed probes rely on wash cycles whose performance must be verified with high-low sequences. For molecular testing, carryover control is especially important, so tip-based systems are usually preferred.
Viscous specimens need slower aspiration and larger tip bores, and some stations offer a specific program for them. Very low volumes may fall below the accurate dispensing range, so the minimum volume should be confirmed against your pediatric or cerebrospinal fluid requirements.
It does not require a laminar flow cabinet, but it should be placed away from strong draughts and operated with gloves and appropriate decontamination, since aerosols may form during pipetting. Laboratories should follow local biosafety guidance for specimen handling.
Labels are usually printed on demand with the specimen identifier, an aliquot number, the date and sometimes a storage position, in a barcode format the LIS can read. Laboratories should test label adhesion and legibility at freezer temperatures, since poor labels cause lost samples.
Heat inactivation at 56 degrees Celsius for about thirty minutes reduces the infectivity of serum and plasma before they are handled in batches or outside a biosafety cabinet, which lowers the risk to staff. It must be validated for each assay, because heating can degrade some analytes and enzymes.
It depends on the primary tube volume, the dead volume of the pipetting system, and the volume required per test. Laboratories usually plan two to four aliquots per serum tube to limit thaw cycles, and the pipetting station should be specified with the minimum deliverable volume that remains accurate.
Bead milling with stainless steel or ceramic beads suits fibrous tissue and tough specimens, while rotor-stator homogenisers handle larger volumes of sputum and tissue quickly. Chemical liquefaction with a reducing agent such as dithiothreitol is often combined with mechanical processing for sputum in mycobacteriology.
Related models